
The standard fertility investigations do not always find a reason. Embryos can look good and hormones normal, yet transfers do not take or pregnancies do not hold, and no one can say why. Clinicians will recognise that cohort. Recurrent implantation failure, recurrent pregnancy loss, and unexplained infertility remain the hardest groups to investigate productively once the standard workup returns normal.
One of the factors increasingly recognised in that space, and increasingly testable, is the microbial environment of the endometrium itself. For most of modern medicine, the uterine cavity was assumed to be sterile. Next-generation sequencing has shown it is not. The endometrium hosts its own microbial community, and its composition is associated with whether implantation succeeds and whether pregnancies are sustained. In a substantial proportion of women with otherwise unexplained fertility difficulties, that community is disrupted.
This is the first in a four-part series on the endometrial microbiome. It covers what the microbiome is, why it was missed for so long, what the evidence shows about its role in fertility, and how BioBloom Life's test measures it.
What the endometrial microbiome is
The endometrial microbiome is the population of bacteria, and to a lesser extent other microorganisms, that live within the uterine cavity.
The biomass is very low compared with other body sites such as the gut. That low density was, for a long time, indistinguishable from laboratory contamination, which is part of why the uterus was thought to be sterile.
In many reproductive-age women, the endometrial community is dominated by Lactobacillus species. “Dominated” has a specific meaning: Lactobacillus accounting for more than 90% of the bacterial community, with the remaining fraction made up of small amounts of other taxa. This >90% threshold, established by Moreno et al., 2016, is the most widely used definition. Some studies apply an 80% cut-off or alternative definitions, and the field has not fully converged on a single standard.
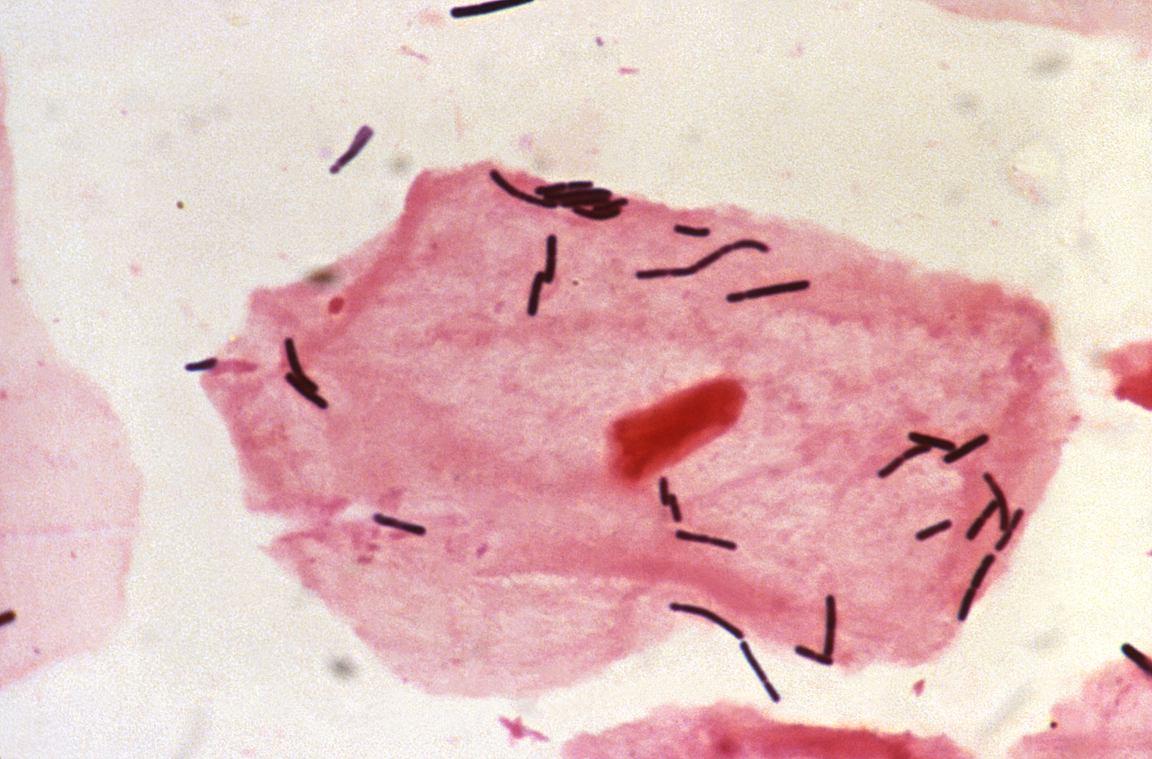
When Lactobacillus dominance falls below this threshold, the community is described as dysbiotic. Other taxa, including Gardnerella, Atopobium, Streptococcus, Prevotella, and Staphylococcus, make up a larger share. Dysbiosis is a pattern, not a diagnosis of infection, and no single organism defines it.
Why it was missed for so long
There are two main reasons.
The sterile-uterus dogma
For decades, textbooks taught that the cervix acted as a barrier keeping the uterus bacterially clean, and that any bacteria found inside were sampling contaminants. That view persisted until 16S rRNA gene sequencing showed consistent, reproducible microbial signals from endometrial samples that could not be explained by contamination. Moreno et al., 2016 (Am J Obstet Gynecol, n=35) was the study that established the endometrial microbiota as a real, measurable entity with reproductive consequences.
The technical bar is high
Detecting a low-biomass community reliably requires next-generation sequencing with strict contamination controls at every step. Reagents, swabs, and the sampling route itself can introduce bacterial DNA that is not from the endometrium. Studies that fail to account for this produce inconsistent results. It is why endometrial microbiome testing remains specialised rather than routine, and why methodology varies significantly between providers.
What the evidence shows
The clinical evidence base has matured rapidly over the last decade. A few of the studies worth knowing:
Moreno et al., 2016 (Am J Obstet Gynecol, n=35)
In IVF patients with a confirmed receptive endometrium, Lactobacillus dominance was associated with significantly better outcomes: live birth rate 58.8% vs 6.7% (p=0.002), ongoing pregnancy 58.8% vs 13.3% (p=0.02), implantation 60.7% vs 23.1% (p=0.02). Small sample, large effect sizes, foundational paper.
Moreno et al., 2022 (Microbiome, n=342)
A multicentre prospective observational study across four continents confirmed that a dysbiotic endometrial profile was associated with unsuccessful outcomes, and that the association held in a large, asymptomatic-for-infection population.
342 patients across 13 ART centres on four continents
Hiratsuka et al., 2025 (Sci Rep, n=73)
In a RIF cohort, endometrial dysbiosis prevalence was 53.4% on sequencing. Dysbiosis, chronic endometritis on hysteroscopy (56.2%), and CD138-positive CE (49.3%) identified largely non-overlapping patient populations, suggesting each test captures a different clinical signal.
Kyono et al., 2019 (Reprod Med Biol, n=92)
All nine treated non-Lactobacillus-dominant patients converted to Lactobacillus dominance after antibiotic plus probiotic therapy; five of the nine (55.6%) subsequently achieved pregnancy.
Cicinelli et al., 2015 (Hum Reprod)
Reported better outcomes at subsequent IVF in women with RIF whose chronic endometritis resolved after antibiotics than in women whose endometritis persisted. The design was observational, so this is an association, not proof that treatment caused the difference. The CE literature overlaps substantially with the microbiome literature, and the two investigations are complementary rather than duplicative.
Key studies
| Study | Finding |
|---|---|
| Moreno 2016 | Live birth rate 58.8% with Lactobacillus-dominant endometrium, versus 6.7% without (n=35). |
| Hiratsuka 2025 | 53.4% of RIF patients in one cohort showed endometrial dysbiosis on sequencing, often missed by hysteroscopy alone (n=73). |
| Cicinelli 2015 | IVF live birth 60.8% after CE resolution with antibiotic therapy, versus 13.3% when CE persists. |
The paper library gives each study’s finding and, where reported, its sample size. See all 18 papers in the library
If a workup has come back normal, the endometrial environment is one of the few areas left to look at. Testing is not first-line, and your fertility specialist can tell you whether it fits your situation.
What “balance” means in the endometrium
A balanced endometrial microbiome is one where Lactobacillus species dominate and other taxa are present only in small amounts. Several mechanisms have been proposed:
- Lactic acid production, which lowers local pH and limits growth of other bacteria
- Modulation of the local immune environment, including reduction of pro-inflammatory signalling
- Competition with potentially pathogenic species for nutrients and binding sites
A dysbiotic endometrium shows the opposite: reduced Lactobacillus, increased diversity of other taxa, and in some studies, elevated inflammatory markers in surrounding tissue. This inflammatory state is one of the proposed mechanisms by which dysbiosis affects implantation.
The language throughout this field is associated with, not causes. The associations are strong and reproducible. Causation remains under investigation.
Why this matters clinically
The endometrium is where implantation happens. Each step of implantation, attachment, invasion, and vascular connection, depends on the endometrium being receptive. Receptivity has traditionally been assessed through endometrial thickness on ultrasound and, more recently, gene-expression profiling. The microbial environment has been largely absent from this picture despite evidence that it affects outcomes independently of embryo quality.
The clinical signal is strongest in three groups:
- Recurrent implantation failure, typically after two or more failed transfers with good-quality embryos
- Recurrent pregnancy loss, particularly early loss
- Unexplained infertility after standard workup has been unrevealing
When testing is worth considering
In each, some patients have endometrial dysbiosis that a standard workup does not look for. For them, a microbiome result adds information that other investigations do not provide.
Endometrial dysbiosis is typically asymptomatic. The clinical signals that prompt consideration of testing are not physical; they are reproductive:
- Unexplained infertility after standard investigations
- Two or more failed IVF cycles with good-quality embryos
- Recurrent pregnancy loss, particularly early loss
- A history of chronic endometritis or repeated intrauterine procedures
- Suspected chronic endometritis, where a biopsy for CD138 histology is planned
How BioBloom Life fits in
BioBloom Life was founded to address a specific gap: the endometrial microbiome matters clinically, but its low biomass makes it hard to measure consistently.
- Built for the endometrium
- Our method is designed for the low-biomass endometrium: negative controls run alongside patient samples, known reagent contaminants are subtracted, and samples below a minimum-biomass threshold are flagged rather than reported.
- Lactobacillus species where the data supports it
- Lactobacillus species, such as L. crispatus and L. iners, are reported where the data supports it, because they have different clinical associations in the published literature.
- Clinician-facing reports
- The report is structured to support discussion between patient and consultant. It is ordered by clinicians and the sample is collected in clinic. It is not a home test.
- Founded at the University of Cambridge
- BioBloom Life was founded at the University of Cambridge, and our endometrial microbiome test is registered with the MHRA as a general IVD. Registered clinics order it through our clinician portal.
Frequently asked questions
How is the sample collected?
A small sample of endometrial tissue is collected from inside the uterus using a thin catheter during a brief outpatient procedure. It is similar to IUI or embryo transfer sample collection and is generally well tolerated. Optimal collection timing is in the secretory phase of the menstrual cycle.
Will a patient have symptoms if the endometrial microbiome is disrupted?
Usually not. Endometrial dysbiosis is typically silent and does not produce physical symptoms. This is part of why it has been historically underdiagnosed, and part of why testing matters in otherwise unexplained cases.
Is endometrial microbiome testing part of standard fertility workup?
Not yet. The evidence base has matured substantially, but in most UK clinics it is currently used selectively, most often in RIF, RPL, and unexplained infertility. Clinical uptake is growing as the evidence base develops.
Can the endometrial microbiome be improved without medical treatment?
The evidence for lifestyle or over-the-counter interventions is limited. The interventions with the strongest evidence, targeted antibiotic therapy followed by Lactobacillus supplementation, are clinician-led. If testing shows dysbiosis, the next step is a conversation with a fertility specialist, not self-management.
Who is this test right for?
Patients with unexplained infertility after standard workup, failed IVF cycles despite good-quality embryos, or recurrent pregnancy loss. For patients earlier in their fertility journey, it is not a first-line test and is better considered once standard investigations are complete.
How do clinicians order the test?
Through the BioBloom Life clinician portal. Once your clinic is registered and your team is set up and trained, your clinicians order the test and read the report there.
Next steps
For clinicians
Methodology, sample specifications, and the evidence base are covered in detail across this four-part series. Use it as the orientation reference when introducing endometrial microbiome testing into your fertility workup.
For patients
If you have had unexplained fertility difficulties and want to understand whether endometrial microbiome testing may add something to your workup, the next step is a conversation with a fertility specialist familiar with microbiome-guided care. Your clinician can register their clinic with BioBloom Life for the test.
References
Moreno I, Codoñer FM, Vilella F, Valbuena D, Martinez-Blanch JF, Jimenez-Almazán J, Alonso R, Alamá P, Remohí J, Pellicer A, Ramon D, Simon C. Evidence that the endometrial microbiota has an effect on implantation success or failure. Am J Obstet Gynecol. 2016;215(6):684-703.
Moreno I, Garcia-Grau I, Perez-Villaroya D, Gonzalez-Monfort M, Bahçeci M, Barrionuevo MJ, et al. Endometrial microbiota composition is associated with reproductive outcome in infertile patients. Microbiome. 2022;10(1):1.
Hiratsuka D, Matsuo M, Kashiwabara K, Inoue M, Ishizawa C, Iida R, Fukui Y, et al. Comparison of diagnostic tests for chronic endometritis and endometrial dysbiosis in recurrent implantation failure: impact on pregnancy outcomes. Sci Rep. 2025;15:8272.
PubMed (opens in a new tab)PMC (opens in a new tab)Research library
Kyono K, Hashimoto T, Kikuchi S, Nagai Y, Sakuraba Y. A pilot study and case reports on endometrial microbiota and pregnancy outcome: an analysis using 16S rRNA gene sequencing among IVF patients, and trial therapeutic intervention for dysbiotic endometrium. Reprod Med Biol. 2019;18(1):72-82.
Cicinelli E, Matteo M, Tinelli R, Lepera A, Alfonso R, Indraccolo U, Marrocchella S, Greco P, Resta L. Prevalence of chronic endometritis in repeated unexplained implantation failure and the IVF success rate after antibiotic therapy. Hum Reprod. 2015;30(2):323-330.
Chen C, Song X, Wei W, Zhong H, Dai J, Lan Z, Li F, et al. The microbiota continuum along the female reproductive tract and its relation to uterine-related diseases. Nat Commun. 2017;8:875.
Every reference above is in our research library, with 12 more papers alongside.
Glossary: terms used in this article
- Lactobacillus-dominant (LD)
- A microbiome where Lactobacillus species make up 90% or more of the bacterial community; associated with favourable reproductive outcomes.
- Dysbiosis
- A disturbed or imbalanced microbial community; in the endometrium, reduced Lactobacillus and a larger share of other bacteria; a pattern rather than a specific infection.
- Chronic endometritis (CE)
- Persistent, usually asymptomatic inflammation of the endometrium; typically diagnosed by CD138-positive plasma cells on biopsy, or by hysteroscopic appearance.
- CD138
- A cell-surface marker used to identify plasma cells in tissue; CD138-positive plasma cells in the endometrium indicate chronic inflammation.
- RIF
- Recurrent implantation failure; typically no pregnancy after two or more embryo transfers of good-quality embryos in a patient under 40.
- RPL
- Recurrent pregnancy loss; two or more consecutive clinical pregnancy losses, typically before mid-pregnancy.
- 16S rRNA sequencing
- A method of identifying bacteria by sequencing a gene shared across nearly all bacterial species; reveals what's present without needing to culture.
- Low biomass
- An environment with very little microbial material; requires specialised sequencing with strict contamination controls; the endometrium is a classic low-biomass site.
- Hysteroscopy
- A procedure where a thin camera is passed through the cervix to visualise the uterine cavity; used to assess CE features among other things.
- Embryo transfer
- The IVF step where one or more embryos are placed into the uterus; the point in the cycle where endometrial receptivity matters most.